Semaglutide improved two important measures of liver tissue damage in ESSENCE, a phase 3 trial involving people with metabolic dysfunction-associated steatohepatitis, or MASH, and moderate-to-advanced fibrosis. The findings support a meaningful treatment effect on biopsy findings—not simply on body weight. They also underpin an FDA accelerated approval for Wegovy injection in adults with MASH and moderate-to-advanced fibrosis. The treatment is therefore not merely investigational for this indication.
The central interpretive question is what improved tissue findings establish about future health. ESSENCE’s planned 72-week analysis measures inflammation and scarring; the longer trial is intended to examine clinical consequences such as liver-related events. This article uses the indexed primary research abstracts and available official FDA material, rather than a review of complete protocols, supplements, or all full texts. That evidence supports a clear account of the interim findings while leaving several consequential questions open.
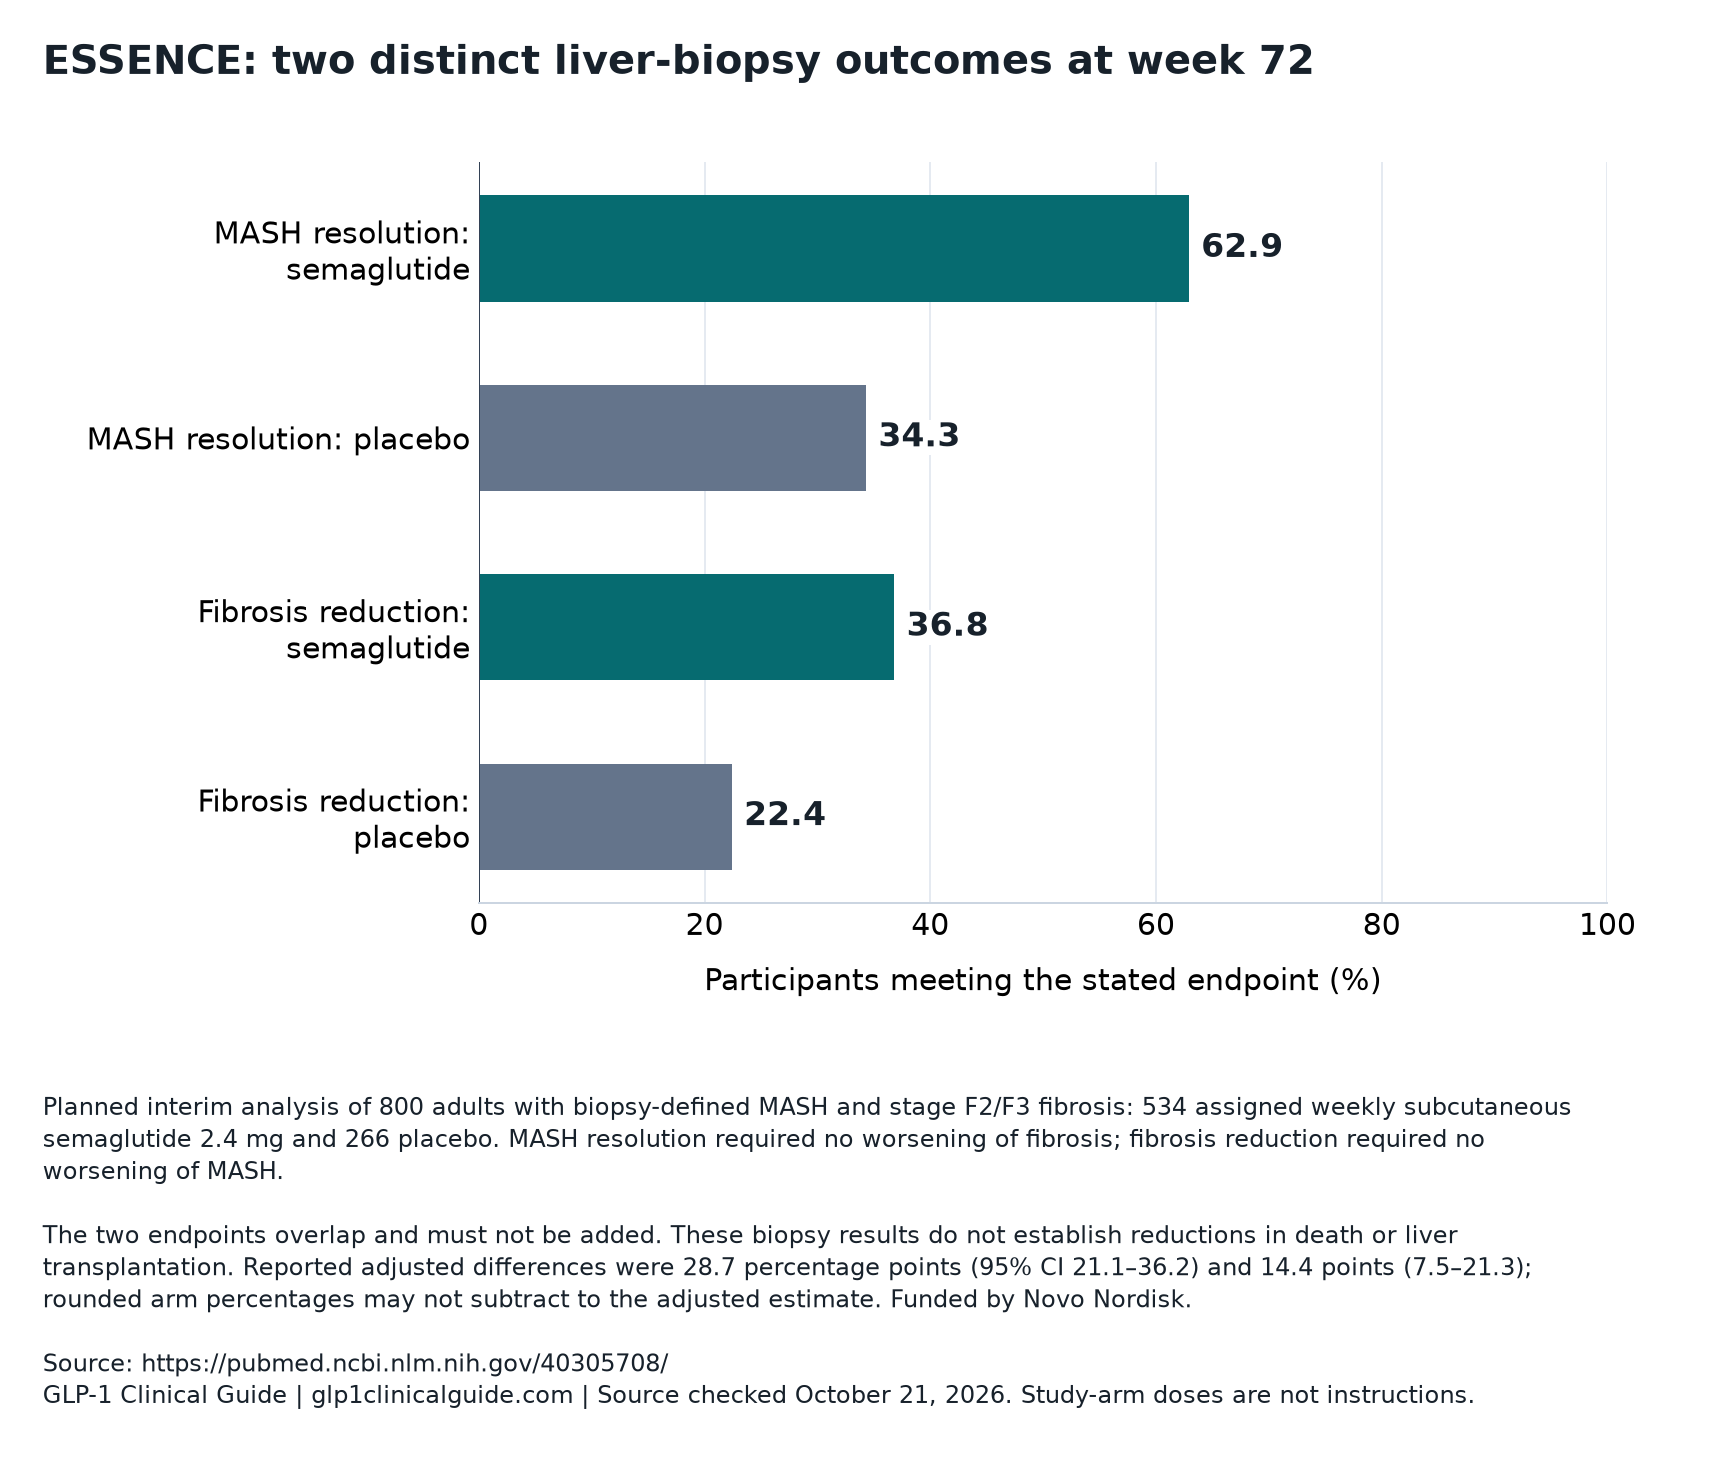
ESSENCE: two distinct liver-biopsy outcomes at week 72
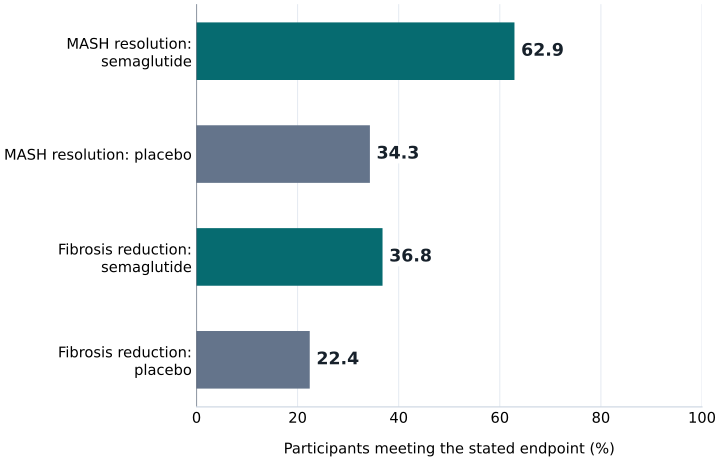
Planned interim analysis of 800 adults with biopsy-defined MASH and stage F2/F3 fibrosis: 534 assigned weekly subcutaneous semaglutide 2.4 mg and 266 placebo. MASH resolution required no worsening of fibrosis; fibrosis reduction required no worsening of MASH.
The two endpoints overlap and must not be added. These biopsy results do not establish reductions in death or liver transplantation. Reported adjusted differences were 28.7 percentage points (95% CI 21.1–36.2) and 14.4 points (7.5–21.3); rounded arm percentages may not subtract to the adjusted estimate. Funded by Novo Nordisk.
Source 1Download the source-labeled chart (PNG) · Download the data (CSV)
| Study group | Reported value |
|---|---|
| MASH resolution: semaglutide | 62.9 |
| MASH resolution: placebo | 34.3 |
| Fibrosis reduction: semaglutide | 36.8 |
| Fibrosis reduction: placebo | 22.4 |
Sections in this article
ESSENCE studied established liver injury, not weight alone
MASH involves liver fat accumulation accompanied by inflammation and tissue injury. Fibrosis means scar tissue; sufficiently advanced scarring can lead to cirrhosis and serious complications. ESSENCE selected participants whose biopsies showed MASH with fibrosis stage F2 or F3, representing moderate or advanced fibrosis without cirrhosis. This was a defined liver-disease population, not a general sample of people seeking weight management.
That distinction determines how broadly the findings travel. The interim report does not establish the same benefit in people with liver fat alone, earlier fibrosis, or cirrhosis. Nor does a body-mass index or a website screening result identify the tissue-defined population studied here. Our guide to what clinical eligibility means explains why a screening threshold and a clinical diagnosis answer different questions.
The FDA describes MASH as a disease that can remain without symptoms until substantial damage develops. Consequently, symptom improvement alone would be an incomplete way to judge treatment. ESSENCE instead asked whether treatment changed liver tissue in people already showing consequential injury—a more disease-specific question than whether participants lost weight or felt better.
Source 1 Source 2How the 72-week comparison was constructed
ESSENCE is a multicenter, randomized, double-blind, placebo-controlled trial funded by Novo Nordisk. Investigators assigned 1,197 participants in a 2:1 ratio to once-weekly subcutaneous semaglutide, at a study dose of 2.4 mg, or placebo for a planned 240 weeks. Subcutaneous means injected under the skin. These doses identify the research arms, not instructions for starting or adjusting treatment.
The published interim analysis concerned the first 800 participants at week 72: 534 assigned semaglutide and 266 placebo. It was a planned analysis, not the final report for all 1,197 participants. The FDA account states that both groups also received lifestyle interventions and that participants were on stable doses of lipid-lowering, glucose-management, and weight-loss medications.
Random assignment makes the comparison more informative than observing treated patients alone, while blinding helps limit differences driven by knowledge of treatment assignment. The placebo group’s substantial improvement also matters: the relevant treatment effect is the difference between groups under trial conditions, not the entire improvement observed in the semaglutide group.
Source 1 Source 2The two primary endpoints ask different questions
The first primary endpoint was resolution of steatohepatitis without worsening fibrosis. In plain language, the inflammatory disease pattern had to resolve while scarring did not deteriorate. Resolution of MASH did not require scar tissue to disappear. The second primary endpoint reversed the emphasis: fibrosis had to improve without worsening steatohepatitis. Neither endpoint is shorthand for a completely normal liver.
Both comparisons favored semaglutide. For resolution, the reported estimated between-group difference was 28.7 percentage points. For fibrosis reduction, it was 14.4 percentage points. Both primary comparisons had reported P values below 0.001. Their confidence intervals excluded zero, supporting a treatment advantage for each endpoint within the trial’s analysis.
The confidence intervals describe uncertainty around the estimated group differences, not the range of responses an individual should expect. The smaller fibrosis difference also deserves attention: improvement in inflammation and improvement in scar tissue are not interchangeable achievements. Our guide, what is this test meant to answer?, offers a useful framework for keeping a measurement separate from the broader clinical question.
| Endpoint | Semaglutide vs placebo | Reported estimated difference, percentage points (95% CI) |
|---|---|---|
| MASH resolution without worsening fibrosis | 62.9% vs 34.3% | 28.7 (21.1–36.2) |
| Fibrosis reduction without worsening MASH | 36.8% vs 22.4% | 14.4 (7.5–21.3) |
| Both MASH resolution and fibrosis reduction | 32.7% vs 16.1% | 16.5 (10.2–22.8) |
Reading the percentages without double-counting benefit
A useful numerical interpretation is that the resolution result corresponds to roughly 29 additional responses per 100 participants assigned semaglutide rather than placebo over 72 weeks, using the reported estimated difference. It does not mean a 28.7% relative reduction in disease. Percentage points describe subtraction between response proportions; relative percentages use a different denominator.
Subtracting the displayed resolution rates gives 28.6 points, whereas the report’s estimated difference is 28.7. The joint endpoint similarly shows 32.7% versus 16.1%, with a reported estimate of 16.5 points. The correct approach is to retain the reported statistical estimates and confidence intervals rather than replace them with arithmetic on rounded displayed percentages. The abstract does not supply enough statistical detail to reconstruct those estimates.
The endpoint groups overlap. A participant with both MASH resolution and fibrosis reduction can contribute to more than one response category. Adding 62.9% and 36.8% would therefore not yield an overall success rate. The joint endpoint directly addresses simultaneous improvement: 32.7% versus 16.1%, a secondary outcome included in the plan to account for multiple statistical comparisons.
Source 1Weight changed substantially, but pain did not clearly improve
Mean body weight fell 10.5% with semaglutide and 2.0% with placebo. The estimated difference was −8.5 percentage points, with a 95% confidence interval from −9.6 to −7.4. These are average percentage changes from baseline, not the proportion of participants who lost weight. Individual responses cannot be recovered from the means alone.
Weight change and the joint biopsy outcome were among three secondary outcomes covered by the multiple-testing plan. The third, bodily pain, did not differ significantly between groups. That result does not establish identical pain experiences, but it does prevent presenting the study as demonstrating a pain benefit. A favorable biopsy result and a noticeable symptom improvement are separate claims.
The trial establishes the effect of assignment to semaglutide under these conditions, not how much of the liver response was caused by weight loss versus other biological effects. FDA describes possible mechanisms beyond weight loss as incompletely understood. The oral-drug evidence reviewed in our ATTAIN-1 analysis concerns another molecule and a weight-centered trial, not an interchangeable demonstration of MASH treatment.
Source 1 Source 2 Source 3Accelerated approval recognizes benefit while preserving a larger question
FDA has approved Wegovy injection for adults with MASH and moderate-to-advanced fibrosis through accelerated approval. This pathway permits approval for serious conditions on a surrogate endpoint while requiring additional data to confirm clinical benefit. A surrogate is a measure used to stand in for an outcome of direct importance to patients; here, biopsy changes serve that role.
The biological rationale is substantial: inflammation and scarring are central features of progressive liver disease. Nevertheless, a better biopsy is not itself proof of fewer transplants, deaths, or episodes of worsening liver function. The FDA announcement states that ESSENCE will continue to 240 weeks to examine whether the earlier tissue improvements translate into reductions in death, transplantation, and other liver-related events.
This distinction is not a claim that biopsy findings are unimportant or that approval lacks evidentiary support. It identifies the level of benefit established by this analysis. The 72-week findings support improved liver histology; the longer clinical-outcome question cannot be answered by substituting the response percentages for future event rates.
Source 1 Source 2SELECT and FLOW answer separate outcome questions
Other semaglutide trials demonstrate why population and endpoint must stay attached to every claim. SELECT enrolled 17,604 adults aged at least 45 with established cardiovascular disease, body-mass index of at least 27, and no diabetes history. Over mean follow-up of 39.8 months, its cardiovascular composite occurred in 6.5% with semaglutide versus 8.0% with placebo.
SELECT’s hazard ratio was 0.80, with a 95% confidence interval of 0.72–0.90. This describes a relative difference in event hazard over follow-up, not a 20-percentage-point absolute reduction. FLOW studied 3,533 people with type 2 diabetes and defined chronic kidney disease. Its primary composite favored semaglutide, with 331 versus 410 first events and a hazard ratio of 0.76, with a 95% confidence interval of 0.66–0.88.
Both were randomized and funded by Novo Nordisk, but neither replaces ESSENCE’s liver-specific outcome assessment. A cardiovascular composite is not a liver endpoint, and FLOW’s composite includes cardiovascular death alongside kidney outcomes. A favorable composite does not establish that every component improved individually. Comparing the trials clarifies evidence categories; it does not rank benefits across dissimilar populations.
| Trial and population | Study treatment and observation | Main endpoint |
|---|---|---|
| ESSENCE: biopsy-defined MASH, F2/F3 fibrosis | 2.4 mg subcutaneously weekly vs placebo; 72-week interim analysis | MASH resolution and fibrosis reduction, each with a no-worsening condition |
| SELECT: established cardiovascular disease, overweight or obesity, no diabetes | 2.4 mg subcutaneously weekly vs placebo; mean follow-up 39.8 months | First cardiovascular death, nonfatal heart attack, or nonfatal stroke |
| FLOW: type 2 diabetes and defined chronic kidney disease | 1.0 mg subcutaneously weekly vs placebo; median follow-up 3.4 years | Kidney failure, sustained kidney-function loss threshold, or kidney-related or cardiovascular death |
Tolerability is part of the result, not an afterthought
ESSENCE reported more gastrointestinal adverse events with semaglutide. The indexed abstract does not give event counts, severity distributions, or discontinuation rates, so it cannot support a numerical estimate of those burdens. The FDA announcement lists common effects including nausea, vomiting, diarrhea, constipation, and abdominal pain, but that broader list should not be mistaken for ESSENCE-specific rates.
Safety findings from other trials illustrate why context matters. In SELECT, adverse events led to permanent treatment discontinuation in 16.6% with semaglutide versus 8.2% with placebo. In FLOW, serious adverse events occurred in 49.6% versus 53.8%. Different populations, follow-up, doses, and safety measures prevent these figures from being combined into a single tolerability estimate for MASH.
The FDA MASH announcement also identifies contraindications involving personal or family history of medullary thyroid cancer, multiple endocrine neoplasia type 2, and known sensitivity to semaglutide or product excipients. That announcement is not complete current prescribing information. A care plan needs ongoing reassessment as well as initial eligibility; what to report at follow-up explains that distinction.
Source 1 Source 2 Source 4 Source 5Product identity limits what can be inferred about access
ESSENCE tested a particular injectable semaglutide regimen. Its results do not automatically establish equivalent MASH outcomes for oral formulations, compounded preparations, or products obtained through any particular provider. The distinction is about evidence, not merely branding: formulation, quality oversight, and clinical delivery are separate from sharing a familiar ingredient name.
FDA states that compounded drugs are not FDA approved and do not undergo its premarket review for safety, effectiveness, and quality. It has received reports of dosing errors with compounded injectable semaglutide, some requiring hospitalization. FDA also distinguishes semaglutide salt forms from the active ingredient in approved drugs. These concerns cannot be converted into comparative event rates without reliable exposure denominators.
Our guide to approved, off-label, and compounded treatment separates these categories. Editorial interpretation: an access comparison should first establish what product and service are actually documented. Readers using the Ro review can check documentary terms without treating that review as evidence that the provider offers the studied product, MASH-specific care, or ESSENCE-like outcomes.
Source 1 Source 6A care budget should track the clinical question being followed
ESSENCE supplies efficacy evidence, not a price schedule or a comparison of care contracts. It does not quantify patients’ testing expenses, insurance coverage, specialist costs, or the economic value of preventing future liver events. Estimating savings from avoided transplantation using the 72-week biopsy response would require an unproven bridge from surrogate response to clinical events.
Editorial interpretation: a useful budget distinguishes medication access from disease assessment and follow-up. The practical questions concern who establishes the diagnosis, what monitoring is intended to answer, who evaluates adverse effects, and which services fall outside a membership or medication charge. These are questions to verify in documentation, not services demonstrated by the trial.
For another documentary comparison, the Form Health review can be used to examine stated terms; the trial confers no provider-specific endorsement. A clear plan should connect each expense to a clinical task rather than promise that a subscription reproduces research care. Unresolved durability and clinical-outcome questions remain scientific issues, not contractual guarantees.
Source 1 Source 2Questions about the evidence
Does MASH resolution mean that liver scarring is gone?
No. The resolution endpoint required steatohepatitis to resolve without fibrosis getting worse. Scarring did not have to improve for that endpoint to count. The separate fibrosis endpoint and the joint endpoint provide different information about tissue response. None should be translated into a claim that every responder had a normal liver.
Source 1Why is the placebo response important?
It shows why the treated group’s response rate is not the treatment effect by itself. Both groups received care within the trial, including lifestyle measures described by FDA. Randomization supports interpreting the between-group difference as the additional effect of assignment to semaglutide under those conditions, without establishing why each placebo participant improved.
Source 1 Source 2Did this analysis show fewer liver transplants or deaths?
The reported 72-week analysis established biopsy improvements, not a reduction in transplantation or death. FDA describes the planned 240-week continuation as examining whether tissue improvements translate into fewer clinical events. That statement concerns what this interim analysis demonstrates, rather than making a claim about all later research.
Source 1 Source 2Can the findings be applied to an oral GLP-1 medicine?
Not automatically. ESSENCE studied weekly injected semaglutide. ATTAIN-1 studied daily oral orforglipron in adults with obesity without diabetes, using weight change as its primary endpoint. Shared GLP-1 receptor activity does not make different molecules, routes, populations, or endpoints interchangeable evidence for MASH treatment.
Source 1 Source 3Was the benefit simply a consequence of weight loss?
The study showed both average weight reduction and better biopsy outcomes, but those parallel findings do not determine the mechanism. The abstract does not separate weight-mediated effects from other possible pathways. FDA explicitly describes potential mechanisms beyond weight loss as incompletely understood, leaving the size of each contribution unresolved.
Source 1 Source 2Editorial assessment
ESSENCE provides strong randomized evidence that weekly injectable semaglutide improved liver histology over 72 weeks in the studied F2/F3 MASH population. Both primary endpoints favored treatment, and the joint response strengthens the finding that inflammation and scarring can improve together. The proper interpretation remains specific: meaningful tissue benefit, gastrointestinal tolerability burdens, and an accelerated approval that preserves the need to confirm clinical benefit. Neither a weight-loss percentage nor a provider contract can substitute for that evidence hierarchy.
Research access and limitations
This analysis draws on indexed primary research abstracts and official FDA material. The accessible ESSENCE abstract does not provide detailed missing-data methods, biopsy adjudication procedures, subgroup estimates, or numerical adverse-event rates. The FDA approval announcement is not complete current prescribing information. No provider-specific effectiveness, cost-effectiveness, or formulation equivalence is established here.
Source notes
Scientific sources checked October 21, 2026. Earlier research and provider sources retain their dated histories below. Provider pages document advertised terms. Study summaries identify the scope of our review.
- Phase 3 Trial of Semaglutide in Metabolic Dysfunction-Associated Steatohepatitis.Indexed original research abstract · Checked 2026-10-21
- FDA approves treatment for serious liver disease known as MASHOfficial FDA page read through web tool; historical approval announcement, not complete current labeling · Checked 2026-10-21
- Orforglipron, an Oral Small-Molecule GLP-1 Receptor Agonist for Obesity Treatment.Indexed original research abstract · Checked 2026-10-21
- Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes.Primary research or official information · Checked 2026-10-21
- Effects of Semaglutide on Chronic Kidney Disease in Patients with Type 2 Diabetes.Primary research or official information · Checked 2026-10-21
- FDA — concerns with unapproved GLP-1 productsMedication safety context · Checked 2026-10-21